
Clinical Trials Gave Me Back My Life: Why NIH-Funded Research Must Continue

Clinical Trials Gave Me Back My Life: Why NIH-Funded Research Must Continue
State: Florida
Congressional District:
Diseases
Blood Disease, Cancer
My Story
Clinical Trials Gave Me Back My Life: Why NIH-Funded Research Must Continue
My name is Julie, and I’m here as a patient whose life has been shaped—and saved—by clinical research. I credit a clinical trial with saving my life. Today, I ask for your continued, unwavering support for the National Institutes of Health and its critical investment in biomedical and clinical research for diseases like Multiple Myeloma. The NIH plays a significant role in supporting research, including clinical trials, which are often conducted in hospital settings.
For people like me, facing Multiple Myeloma, that research is not abstract policy—it’s survival.
In October 2020, I was diagnosed with high-risk Multiple Myeloma, a type of blood cancer that tends to progress more quickly and may not respond as effectively to standard treatments. A scan revealed plasmacytomas—tumors—on my pancreas and chest.
Within the first year of my diagnosis, standard-of-care drug regimens couldn’t control my disease. During that year, I went through four lines of treatment, including a stem cell transplant, and none of them sustained my remission for more than a couple of months. I was anxious and scared, wondering if anything would work.
I had to decide whether to start another standard treatment or consider a clinical trial. I spoke with a few other patients who had participated in clinical trials to help with my decision. One had taken part in the original trial for Revlimid; another had been in the original CAR T trial at the NIH. Both were grateful for the opportunity—and more importantly, those treatments put them in long-term remissions while advancing science and helping others.
My doctors suggested the “hot” new therapy using my body’s own immune system to fight the disease: CAR T. At the time, CAR T was not yet FDA-approved for Multiple Myeloma, though it would be a few months later. Sadly, the supply chain issue meant there were no slots available. I couldn’t wait—my disease was progressing rapidly.
A doctor on my team referred me to the Director of Clinical Trials at Mount Sinai, where there might be a trial for me. A Zoom call with him led me to the Talquetamab clinical trial, a bispecific antibody. I was eligible and joined the trial in September 2022, hoping it might save me and help others.
The Talquetamab trial began with a 35-page consent form, screenings, hospital admissions, and intense side effects. I had to stay inpatient for 10 days due to the risk of cytokine release syndrome (CRS). Talquetamab was tough. The skin on my hands and feet peeled. I lost my sense of taste, my mouth dried out, and my fingernails fell off.
But I was willing to endure all of it—for hope. It was a trial made possible by years of NIH-backed research and funding.
Ultimately, the treatment didn’t stop my disease—but it led me to another clinical trial at Mount Sinai. This time, it was a Phase 1 trial with another bispecific antibody called Cevostamab.
Cevostamab was different. The side effects were manageable. I received infusions every three weeks. For the first time, I could live my life between treatments. I traveled, spent time with family, and felt like myself again. This protocol gave me hope—and, more importantly, it worked.
I responded almost immediately to the treatment. After 17 cycles—about a year—my last treatment was December 1, 2022. I’ve been in stringent complete response and MRD-negative since. I am not taking any medication. The research team and my doctor continue to monitor me.
That remission would not have been possible without the clinical trial at Mount Sinai.
This isn’t just about one patient: it’s about all of us.
Every step of my treatment—the labs, the trial design, the science behind the antibodies—was built on NIH-supported research. These innovations don’t come from thin air. They come from sustained, protected federal investment in biomedical science.
Time will tell when and how Cevostamab will be FDA-approved. Until then, clinical trials are the only access. Without NIH funding, those trials stall—and promising therapies don’t reach patients in time.
Securing NIH funding doesn’t just advance science—it delivers hope to thousands of patients with relapsed, aggressive cancers like mine.
I don’t know what my future holds. Multiple Myeloma is still incurable. I live with that uncertainty every day. But here’s what I do know: I am alive—hopeful and grateful—because of clinical research supported by NIH funding.
We must secure and expand that funding—not just for me, but for every patient sitting in a clinic right now, wondering if their next treatment will work.
Please continue to champion this cause. You are funding futures—and I am one of them. Today, I enjoy giving back through my volunteer work as a Myeloma Coach, contributing to my Myeloma support group as a member of the steering and program committees, and participating in community fundraisers for several nonprofit myeloma organizations.
Thank you.
My Motivation and Inspiration
A clinical research trial saved my life after standard care regimens could not control my disease.
Share This Story

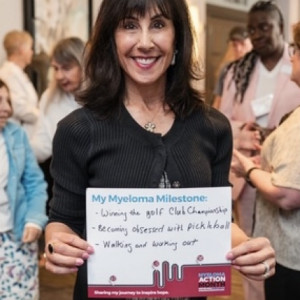


Get the most from every Story
Find A Compelling Patient Story
Share it on social media.
Share Your Story On Our Network
Share your insights, challenges and what keeps you going.